8% Off
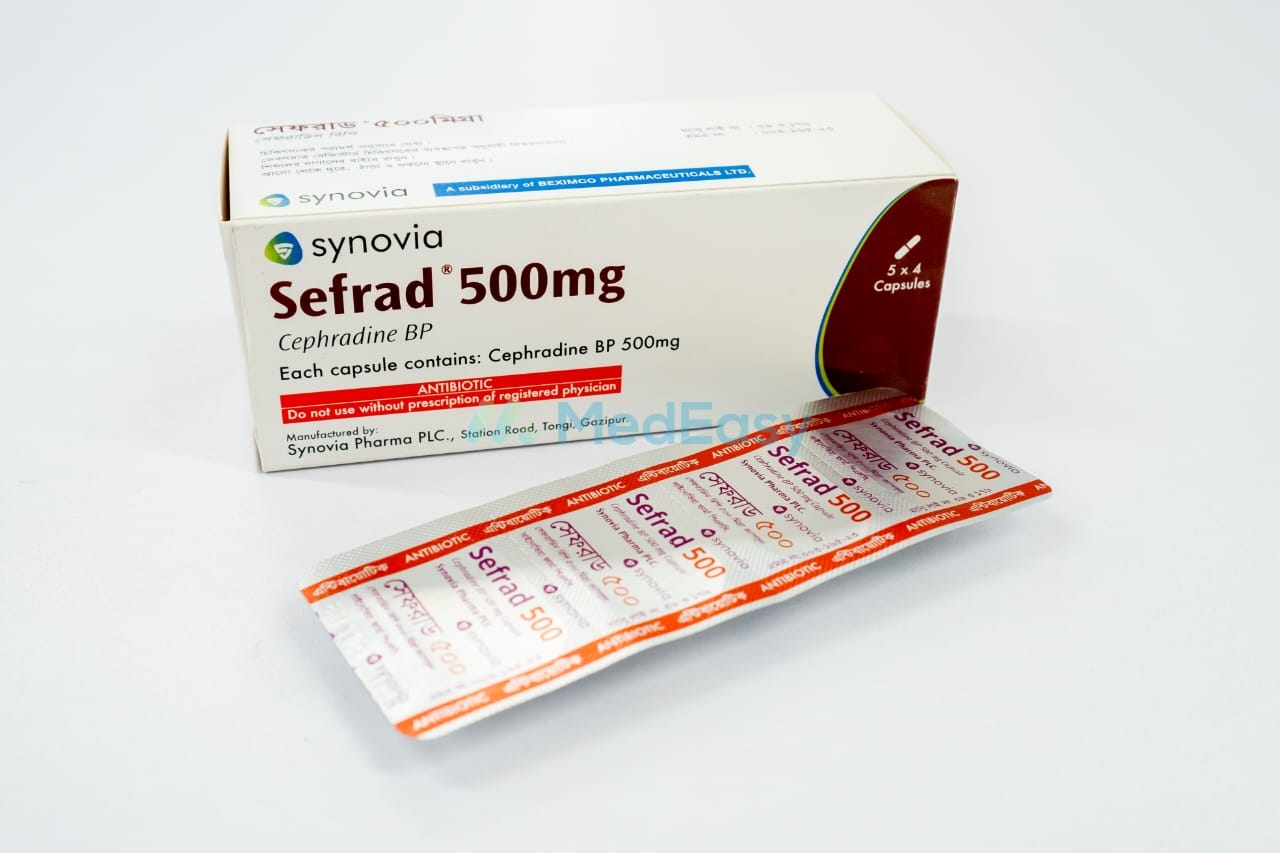
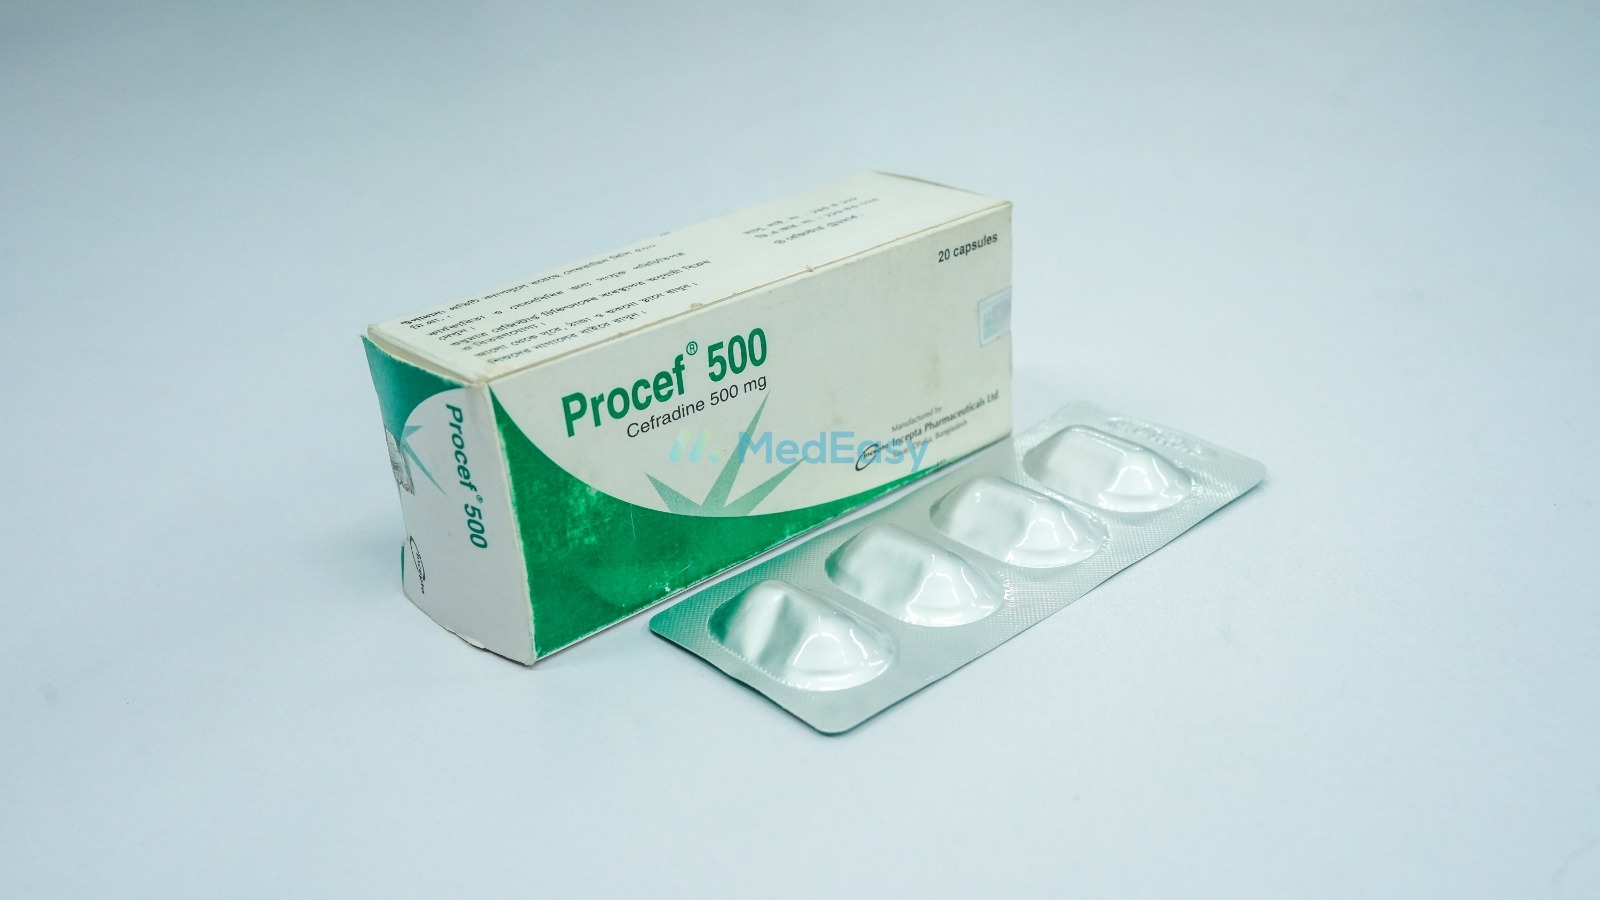
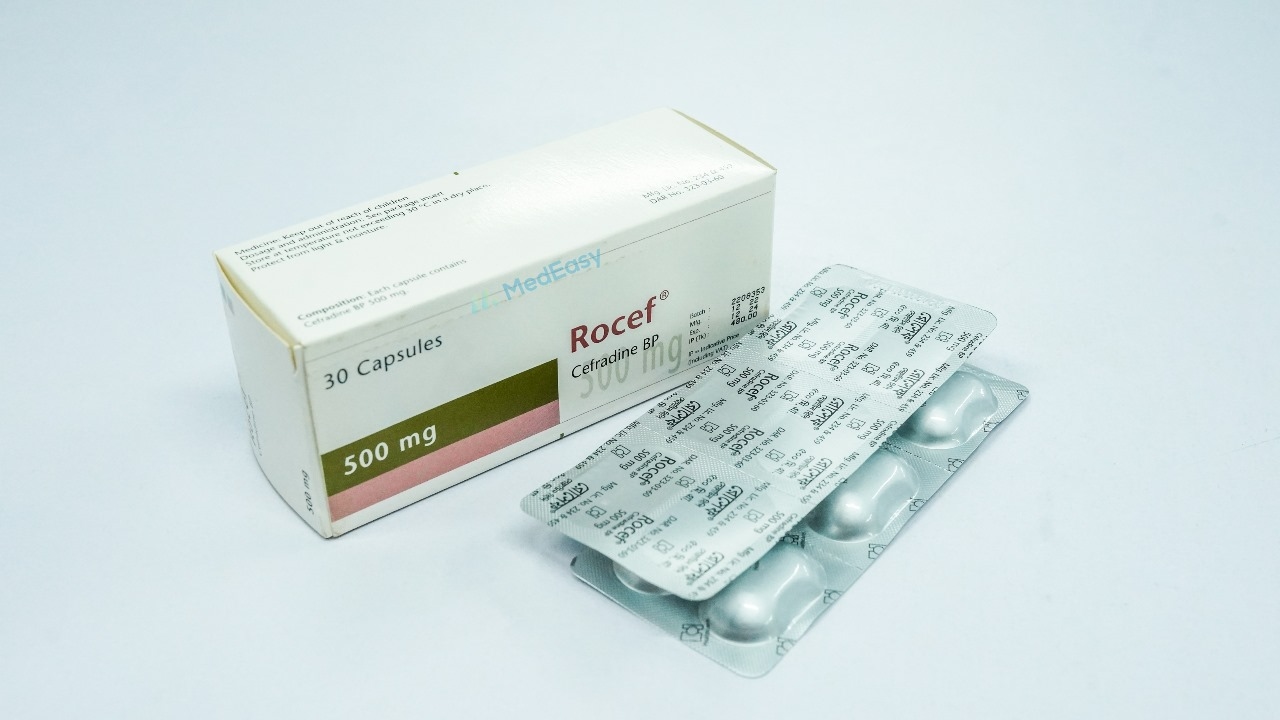
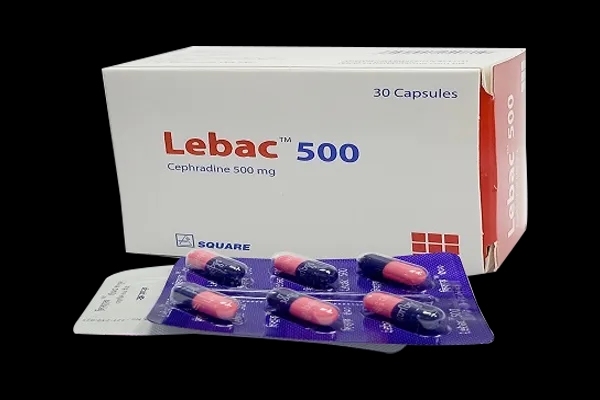
Lebac500 mg
Square Pharmaceuticals PLC.
৳13.85
Add to cart


Alfradin is an established treatment for susceptible upper and lower respiratory tract infections, including pharyngitis, tonsillitis, otitis media, and lobar pneumonia caused by susceptible strains of Streptococcus pneumoniae, Streptococcus pyogenes (Group A beta-hemolytic streptococci), Staphylococcus aureus (including penicillinase-producing strains), and Haemophilus influenzae. For streptococcal pharyngitis/tonsillitis, penicillin or amoxicillin remain the guideline-preferred first-line agents; Alfradin is an alternative for patients who cannot take a penicillin for reasons other than immediate/severe (anaphylactic-type) hypersensitivity.
Alfradin is an established treatment for uncomplicated skin and soft tissue infections caused by susceptible staphylococci and streptococci.
Alfradin is an established treatment for uncomplicated and, at higher doses, complicated urinary tract infections, including cystitis and prostatitis, caused by susceptible organisms such as Escherichia coli, Proteus mirabilis, and Klebsiella pneumoniae.
Alfradin has guideline- and practice-supported use as a treatment option for susceptible bone and joint infections, generally as a narrower-spectrum alternative once causative organism and susceptibility are known; it is not typically first-line empiric therapy for serious bone/joint infection.
The injectable form of Alfradin is used as an adjunct, short-course perioperative antibiotic to reduce the risk of postoperative infection in contaminated or potentially contaminated surgery; it is given as prophylaxis around the time of surgery rather than as prolonged treatment, consistent with antibiotic stewardship principles.
Alfradin is not effective against methicillin-resistant staphylococci, Pseudomonas aeruginosa, most Enterococcus species, or viral, fungal, or parasitic infections, and should be reserved for infections known or strongly suspected to be caused by susceptible bacteria.
Cephradine is available in several strengths and dosage forms, including capsules (250 mg and 500 mg), oral suspension (125 mg/5 mL and 250 mg/5 mL after reconstitution), pediatric oral drops, and injectable powder for reconstitution (250 mg, 500 mg, and 1 g vials), depending on the manufacturer and market.
Alfradin is a semisynthetic, first-generation cephalosporin antibiotic belonging to the beta-lactam class of medicines. Alfradin is bactericidal, meaning it kills susceptible bacteria rather than merely stopping their growth, by interfering with the formation of the bacterial cell wall. Alfradin is commonly prescribed for respiratory tract infections, skin and soft tissue infections, urinary tract infections, and certain bone and joint infections caused by susceptible organisms. Alfradin does not treat viral infections such as the common cold or flu, and Alfradin should be taken exactly as prescribed by a qualified healthcare professional.
Alfradin belongs to the therapeutic class of first-generation cephalosporin antibiotics (beta-lactam class).
Cephradine is a bactericidal, semisynthetic first-generation cephalosporin. Cephradine acts by binding to penicillin-binding proteins (PBPs) located on the bacterial cell membrane, thereby inhibiting the transpeptidation (cross-linking) step of bacterial cell wall (peptidoglycan) synthesis. This weakens the cell wall, leading to cell lysis and death of susceptible, actively dividing bacteria. Cephradine retains activity against many penicillinase-producing strains of Staphylococcus aureus because of relative stability to certain staphylococcal beta-lactamases, although it is not stable against many broader-spectrum beta-lactamases produced by gram-negative organisms.
Cephradine is well absorbed after oral administration, is widely distributed in body tissues and fluids, undergoes minimal metabolism, and is eliminated primarily unchanged by the kidneys through glomerular filtration and tubular secretion. Because renal elimination is the major route of clearance, dosing of Cephradine requires adjustment in patients with reduced kidney function (see Use in Special Populations).
The dose, frequency, and duration of Alfradin vary by indication, patient age, weight, and kidney function, and must be individualized by a qualified healthcare professional. Antibiotic stewardship is essential: take Alfradin exactly as prescribed by your physician; do not stop, extend, skip doses, or share Alfradin with others without medical advice, even if symptoms improve before the course is finished.
| Indication | Adult Dose | Pediatric Dose (over 9 months) |
|---|---|---|
| Respiratory tract and skin/soft tissue infections | 250–500 mg every 6 hours, or 500 mg–1 g every 12 hours | 25–50 mg/kg/day in divided doses every 6–12 hours |
| Lobar pneumonia | 500 mg every 6 hours, or 1 g every 12 hours | 25–50 mg/kg/day in divided doses |
| Otitis media | Not typically an adult indication | 75–100 mg/kg/day in divided doses every 6–12 hours (not to exceed 4 g/day) |
| Uncomplicated urinary tract infection (cystitis) | 500 mg every 12 hours | 25–50 mg/kg/day in divided doses |
| Complicated urinary tract infection / prostatitis | 500 mg every 6 hours, or 1 g every 12 hours | Not established |
| Injectable (moderate to severe infections) | 2–4 g/day in divided doses (up to 8 g/day in life-threatening infection, by IM or slow IV) | 50–100 mg/kg/day in divided doses (up to 300 mg/kg/day in severe infection, under close medical supervision) |
| Perioperative surgical prophylaxis (injectable) | 1–2 g given shortly before surgery, as a short course | Not established |
For streptococcal pharyngitis/tonsillitis, treatment with Alfradin should continue for at least 10 days to reduce the risk of rheumatic fever and post-streptococcal glomerulonephritis. For most other infections, Alfradin is generally continued for at least 48–72 hours after the patient becomes asymptomatic or evidence of bacterial eradication is obtained (see Duration of Treatment). Dosing of Alfradin must be reduced in patients with renal impairment (see Use in Special Populations).
Cephradine is contraindicated in patients with known hypersensitivity to Cephradine or to any other cephalosporin-class antibiotic.
Alfradin is classified in FDA legacy Pregnancy Category B: animal reproduction studies have not shown evidence of fetal harm, but there are no adequate and well-controlled studies in pregnant women. Alfradin, like other cephalosporins, is generally considered an acceptable option in pregnancy when a penicillin cannot be used and treatment of a bacterial infection is clearly needed, but Alfradin should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus, and only under the direct guidance of a qualified healthcare professional.
Alfradin is excreted in breast milk in small amounts. Although serious effects in breastfed infants are not well documented, Alfradin should be used with caution during breastfeeding, and the infant should be monitored for possible effects such as diarrhea, diaper rash, or oral thrush from disturbance of normal gut flora. A physician should be consulted before using Alfradin while breastfeeding.
Reported effects of Alfradin overdose are generally an extension of its common side effects, particularly nausea, vomiting, diarrhea, and other gastric upset; neuromuscular excitability or seizures could theoretically occur with very large doses, especially in patients with renal impairment, as with other beta-lactam antibiotics. There is no specific antidote for Alfradin overdose. If an overdose of Alfradin is suspected, seek immediate medical attention or contact a poison control center; gastric lavage may be considered by medical staff soon after a large recent ingestion. Management is otherwise supportive and symptomatic, and hemodialysis can help remove Alfradin from the body in cases of significant renal impairment or severe overdose.
Store Alfradin capsules and unreconstituted powder at room temperature (below 30°C), away from direct light and moisture, in the original container, and out of the reach and sight of children. Once the oral suspension of Alfradin has been reconstituted with water, it should be kept tightly closed and used within 7 days if stored at room temperature or within 14 days if refrigerated (2–8°C); shake well before each use and discard any unused portion after this time. Reconstituted injectable Alfradin solutions have a much shorter stability and should be used promptly as directed by the healthcare provider preparing them. Do not use Alfradin beyond its expiry date.
Alfradin is approved for use in infants over 9 months of age and older children, dosed on a weight basis (see Pediatric Uses). Adequate data supporting twice-daily dosing regimens of Alfradin in infants under 9 months of age are not available, so Alfradin should be used with particular caution, and generally more frequent dosing, in this younger age group under close medical supervision.
No specific dose adjustment of Alfradin is required for older adults on the basis of age alone, but because renal function commonly declines with age, elderly patients should have their kidney function assessed, and the dose of Alfradin adjusted accordingly if renal impairment is present.
Because Alfradin is cleared mainly by the kidneys, the dosing interval and/or dose must be reduced in renal impairment to avoid accumulation:
| Creatinine Clearance | Suggested Alfradin Dosing |
|---|---|
| Greater than 20 mL/min | 500 mg every 6 hours |
| 5–20 mL/min | 250 mg every 6 hours |
| Less than 5 mL/min | 250 mg every 12 hours, extended up to every 50–70 hours between doses depending on severity |
Patients on hemodialysis should have the dose and timing of Alfradin individualized by their nephrologist/physician in relation to dialysis sessions.
Alfradin is eliminated mainly by the kidneys rather than the liver, and specific dose adjustment for hepatic impairment alone is not well established; Alfradin can generally be used at standard doses in patients with liver impairment and normal renal function, under medical supervision.
See the Pregnancy and Lactation section above for detailed guidance on the use of Alfradin in this population.
The duration of treatment with Alfradin is set by the prescriber and depends on the indication and clinical response. As a general guide, Alfradin is continued for at least 48–72 hours after the patient becomes asymptomatic or there is evidence the infection has resolved. An important exception is streptococcal (Group A beta-hemolytic streptococcus) pharyngitis/tonsillitis, for which Alfradin should be given for a minimum of 10 days to reduce the risk of rheumatic fever and post-streptococcal glomerulonephritis, even though symptoms often improve earlier. Perioperative prophylactic use of Alfradin is limited to a short course around the time of surgery rather than prolonged treatment. Patients should take Alfradin for exactly as long as prescribed and should not stop, extend, or repeat a course of Alfradin without medical advice.
Powder for oral suspension of Alfradin must be reconstituted before use: add the amount of water specified on the product label in two portions, shaking well after each addition, to obtain a uniform suspension (typically providing 125 mg/5 mL or 250 mg/5 mL of Alfradin). Once reconstituted, store the suspension of Alfradin as directed (see Storage Conditions) and shake well before each dose. Injectable Alfradin powder for solution is reconstituted by a healthcare professional with sterile water for injection or another appropriate diluent, according to the vial strength and route (intramuscular or intravenous) directed by the prescriber, and should be used promptly after reconstitution.
First-generation cephalosporin antibiotic (beta-lactam class).
Cephradine is bactericidal. Cephradine binds to penicillin-binding proteins (PBPs) in the bacterial cell membrane and inhibits the transpeptidation (cross-linking) reaction required for bacterial cell wall (peptidoglycan) synthesis. Without an intact cell wall, susceptible bacteria are unable to withstand osmotic pressure, leading to cell lysis and death. Cephradine is relatively stable against certain penicillinases produced by staphylococci, which allows it to remain active against many penicillin-resistant staphylococcal strains, though it is not active against methicillin-resistant staphylococci or organisms producing broader-spectrum beta-lactamases.
B
Alfradin is approved for use in infants over 9 months of age and older children. Standard pediatric dosing of Alfradin for respiratory tract, skin/soft tissue, and urinary tract infections is 25–50 mg/kg/day given in divided doses every 6 to 12 hours. For otitis media caused by Haemophilus influenzae, a higher dose of 75–100 mg/kg/day in divided doses every 6 to 12 hours is used, not exceeding 4 g/day. For more severe infections requiring the injectable form, doses of 50–100 mg/kg/day (up to 300 mg/kg/day in severe, life-threatening infection) may be used under close medical supervision. Adequate data supporting twice-daily dosing of Alfradin in infants younger than 9 months are not available, and safety and efficacy of such regimens in this younger age group have not been established; Alfradin should be used in infants under 9 months only when a physician judges it necessary, with appropriate monitoring. As with adults, a full prescribed course of Alfradin should be completed in children, and antibiotic stewardship principles apply equally to pediatric use.
Q: What is Alfradin 500 mg Capsule used for?
A: Alfradin 500 mg Capsule is a first-generation cephalosporin antibiotic used to treat bacterial infections caused by susceptible organisms, including respiratory tract infections (such as pharyngitis, tonsillitis, otitis media, and pneumonia), skin and soft tissue infections, urinary tract infections, and certain bone and joint infections. Alfradin 500 mg Capsule does not treat viral infections such as the common cold or flu.
Q: What is the usual dose of Alfradin 500 mg Capsule?
A: For most adult infections taken by mouth, Alfradin 500 mg Capsule is typically given as 250–500 mg every 6 hours or 500 mg–1 g every 12 hours; children over 9 months are usually dosed at 25–50 mg/kg/day in divided doses, with higher doses used for otitis media. The exact dose, frequency, and duration of Alfradin 500 mg Capsule depend on the specific infection, the patient's age, weight, and kidney function, and should always be determined by a qualified healthcare professional.
Q: Can I stop taking Alfradin 500 mg Capsule once I feel better?
A: No. You should take Alfradin 500 mg Capsule exactly as prescribed by your physician and complete the full course, even if your symptoms improve early. Stopping Alfradin 500 mg Capsule too soon, skipping doses, or sharing it with others can allow the infection to return or worsen and contributes to antibiotic resistance; for streptococcal throat infections in particular, a full 10-day course of Alfradin 500 mg Capsule is needed to prevent complications such as rheumatic fever.
Q: Is Alfradin 500 mg Capsule safe if I am allergic to penicillin?
A: Alfradin 500 mg Capsule belongs to the cephalosporin family, which is chemically related to penicillins, and cross-reactivity can occur. Alfradin 500 mg Capsule should be avoided in patients with a history of a severe or immediate allergic reaction (such as anaphylaxis, hives, or breathing difficulty) to a penicillin, and used with caution in patients with milder penicillin allergy history, under medical supervision. Always tell your doctor about any past drug allergies before starting Alfradin 500 mg Capsule.
Q: Can Alfradin 500 mg Capsule be taken during pregnancy or while breastfeeding?
A: Alfradin 500 mg Capsule is classified as FDA Pregnancy Category B and is generally considered an acceptable antibiotic option during pregnancy when clearly needed and no suitable alternative exists, but it should only be used if the potential benefit justifies the potential risk, under a physician's guidance. Alfradin 500 mg Capsule passes into breast milk in small amounts, so it should be used with caution while breastfeeding, and the infant should be watched for diarrhea or thrush; consult your doctor before use in either situation.
Q: What are the common side effects of Alfradin 500 mg Capsule?
A: The most common side effects of Alfradin 500 mg Capsule are nausea, vomiting, diarrhea, stomach discomfort, and mild skin rash. Less commonly, Alfradin 500 mg Capsule can cause vaginal itching or discharge, oral thrush, or mild changes in blood counts. Severe or persistent diarrhea, signs of a severe allergic reaction, or yellowing of the skin or eyes while taking Alfradin 500 mg Capsule should be reported to a doctor immediately; see the Side Effects section above for full details.
Disclaimer
The information provided is accurate to the best of our knowledge, but it does not replace professional medical advice. We cannot guarantee its completeness or accuracy, and the absence of specific information about a drug should not be taken as an endorsement. We are not responsible for any consequences arising from this information, so please consult a healthcare professional for any concerns or questions.