
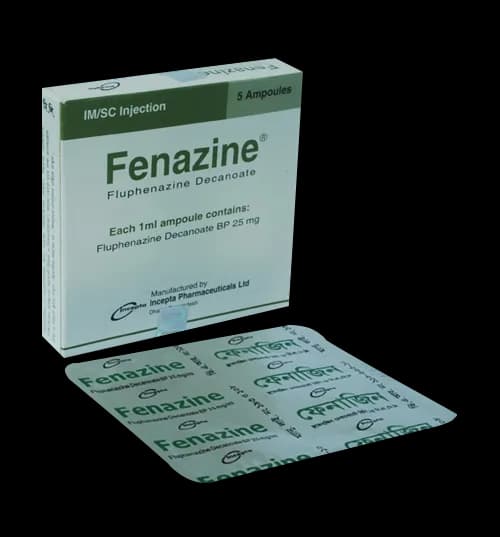

Medicine overview
Indications of Fenazine
Fenazine is a long-acting (depot) injectable formulation of the first-generation (typical) antipsychotic fluphenazine, esterified with decanoic acid to allow slow release from an intramuscular or subcutaneous depot.
Established / FDA-approved use
- Maintenance treatment of schizophrenia in patients who require prolonged parenteral neuroleptic therapy, particularly patients with chronic psychotic symptoms who benefit from a long-acting formulation because of adherence difficulties with daily oral therapy.
Important scope limitations (per approved labeling)
- Fenazine has not been shown to be effective for managing behavioral complications in patients with intellectual disability.
- It is not approved for treating dementia-related psychosis in elderly patients (see Precautions and Warnings for the boxed mortality warning).
Because of its delayed onset (effects generally begin 24–72 hours after injection) and long duration of action, Fenazine is generally not used to treat acute psychotic agitation; patients are usually stabilised first on a shorter-acting form of fluphenazine before being converted to the decanoate depot.
Composition
Each mL of Fluphenazine Decanoate injection typically contains fluphenazine decanoate 25 mg in a sesame oil vehicle, with benzyl alcohol as a preservative. Strength and pack size may vary by manufacturer/brand; always check the product label of the dispensed brand.
Description
Fenazine is the decanoate ester of fluphenazine, a trifluoromethyl phenothiazine derivative belonging to the first-generation ("typical") antipsychotic class. Esterification of the fluphenazine molecule with decanoic acid, and formulation in an oily vehicle, markedly slows release and absorption after intramuscular or subcutaneous injection, converting a drug that would otherwise need daily oral dosing into a depot product that is typically injected once every 2 to 4 weeks (up to 100 mg per dose, per approved labeling).
Fenazine is used for long-term maintenance therapy of schizophrenia, particularly in patients for whom adherence to daily oral antipsychotic therapy is a concern.
Therapeutic Class
Fenazine belongs to the phenothiazine class of first-generation (typical) antipsychotics, specifically the piperazine phenothiazine subgroup. It is classified as a long-acting (depot) injectable antipsychotic.
Pharmacology
The precise mechanism by which Fluphenazine Decanoate produces its antipsychotic effect is not fully established, but its principal pharmacological action is thought to be post-synaptic dopamine D2-receptor antagonism in the mesolimbic and mesocortical pathways of the central nervous system, which is believed to underlie its efficacy against positive psychotic symptoms (hallucinations, delusions, disorganised thinking).
Fluphenazine also has antagonist activity at alpha-adrenergic, histaminic (H1), and, to a lesser degree, muscarinic cholinergic receptors, which contributes to some of its adverse effect profile (e.g., orthostatic hypotension, sedation). Blockade of dopamine receptors in the nigrostriatal pathway is responsible for extrapyramidal symptoms, and blockade in the tuberoinfundibular pathway raises prolactin.
Pharmacokinetics
- Absorption: Esterification and the oily depot vehicle produce slow, sustained release from the injection site; onset of clinical effect is generally seen 24–72 hours after injection.
- Duration: A single injection of Fluphenazine Decanoate may control symptoms for up to 4 weeks or longer, allowing dosing intervals of roughly 2–4 weeks in most patients.
- Metabolism: The decanoate ester is gradually hydrolysed to free fluphenazine, which undergoes hepatic metabolism.
- Elimination: Because the drug is released slowly from the depot, its effects (both therapeutic and adverse) persist for a prolonged period after the last injection and cannot be rapidly reversed by discontinuing the drug.
Dosage & Administration of Fenazine
Route of administration
Fenazine is given by deep intramuscular or subcutaneous injection only. It must never be given intravenously. A dry syringe and needle (minimum 21-gauge) should be used, as moisture can cause the solution to become cloudy.
Adult dosing — maintenance treatment of schizophrenia
| Step | Typical dose | Notes |
|---|---|---|
| Initial dose | 12.5 mg to 25 mg (0.5–1 mL) IM or SC | Onset of action generally 24–72 hours after injection. |
| Maintenance dose | 12.5 mg to 25 mg every 2–4 weeks (individualised) | Interval and dose adjusted based on clinical response; some patients may need doses up to a maximum of 100 mg per injection. |
| Dose increases | In increments of about 12.5 mg | Doses above 50 mg should be increased cautiously. |
Conversion from oral fluphenazine
There is no precise conversion formula. Clinical experience suggests roughly 10 mg of oral fluphenazine hydrochloride per day corresponds approximately to 12.5 mg of Fenazine given every 3 weeks, but the physician individualises the actual regimen. Patients who have not previously received fluphenazine should first be treated with a shorter-acting oral or injectable form to establish tolerability before starting Fenazine.
Pediatric dosing
Fenazine is not recommended for children under 12 years of age; safety and efficacy in the pediatric population have not been established (see Use in Special Populations).
Renal/hepatic impairment
No well-established dose-adjustment schedule exists for renal or hepatic impairment; Fenazine is contraindicated in severe liver disease (see Contraindications), and should be used with caution and close monitoring of hepatic function in patients with any degree of hepatic impairment.
Administration of Fenazine
Fenazine must be administered only by a trained healthcare professional, by deep intramuscular or subcutaneous injection — never intravenously. Use a dry syringe and needle of at least 21-gauge; a wet needle or syringe can cause the oily solution to turn cloudy. Rotate injection sites. Patients should be observed after the first dose for hypersensitivity or unusual reactions, and monitored periodically for extrapyramidal symptoms and other adverse effects for as long as the depot effect persists.
Interaction of Fenazine
The following interactions with Fenazine are clinically significant and well documented for phenothiazine antipsychotics:
- CNS depressants (alcohol, opioids, barbiturates, benzodiazepines, general anesthetics): Fenazine potentiates the sedative and respiratory-depressant effects of these agents; concurrent use should be avoided or closely monitored.
- Other QT-prolonging drugs (e.g., certain antiarrhythmics, other antipsychotics, some antibiotics): additive risk of QT-interval prolongation and torsades de pointes; combination should be avoided where possible.
- Anticholinergic agents: additive anticholinergic effects (dry mouth, constipation, urinary retention, blurred vision) may occur with concurrent use.
- Antihypertensive agents: Fenazine can cause orthostatic hypotension and may potentiate the hypotensive effect of antihypertensive drugs.
- Drugs that lower seizure threshold: Fenazine itself can lower seizure threshold; caution is needed when combined with other agents that do the same (e.g., tramadol, bupropion).
- Lithium: rare reports of an encephalopathic syndrome (confusion, weakness, extrapyramidal symptoms) with concurrent phenothiazine and lithium use; monitor closely if combined.
Contraindications
Fluphenazine Decanoate is contraindicated in:
- Known hypersensitivity to fluphenazine or to any other phenothiazine (cross-sensitivity among phenothiazines may occur).
- Comatose states or severe CNS depression from any cause.
- Circulatory collapse.
- Pre-existing blood dyscrasias.
- Suspected or established subcortical brain damage.
- Severe hepatic disease.
- Severe cardiovascular disease.
- Concurrent use with large doses of hypnotic (CNS-depressant) agents.
Fluphenazine Decanoate should not be used to treat dementia-related psychosis in elderly patients (see boxed warning under Precautions and Warnings), and is not recommended in children under 12 years of age.
Side Effects of Fenazine
Adverse effects of Fenazine are generally similar to those of oral fluphenazine, but because it is a long-acting depot injection, any reaction that occurs — including hypersensitivity and extrapyramidal reactions — may take considerably longer to resolve than with an oral dose, since the drug cannot be immediately withdrawn from the body.
Common
- Extrapyramidal symptoms — pseudoparkinsonism (tremor, rigidity), dystonia, akathisia (restlessness), oculogyric crisis
- Drowsiness, sedation, lethargy
- Dry mouth, constipation, blurred vision, nasal congestion
- Orthostatic hypotension, dizziness
- Weight gain
Less common but clinically important
- Tardive dyskinesia — potentially irreversible involuntary movements; risk rises with cumulative dose and duration of treatment (see Precautions and Warnings).
- Neuroleptic malignant syndrome (NMS) — a rare, potentially fatal reaction with hyperthermia, muscle rigidity, altered mental status, and autonomic instability; requires immediate medical attention.
- Elevated prolactin — menstrual irregularities, galactorrhea, gynecomastia, decreased libido.
- QT-interval prolongation and, rarely, serious arrhythmia.
- Leukopenia, neutropenia, or (rarely) agranulocytosis, especially in the initial months of therapy.
- Cholestatic jaundice, mainly in the first months of treatment.
- Skin reactions including photosensitivity, urticaria, and rarely exfoliative dermatitis.
- Seizures (in patients with a lowered seizure threshold).
Pregnancy & Lactation
Pregnancy: Adequate, well-controlled studies of Fenazine in pregnant women are not available. Neonates exposed to antipsychotic drugs, including Fenazine, during the third trimester are at risk of extrapyramidal and/or withdrawal symptoms after delivery, including agitation, abnormally increased or decreased muscle tone, tremor, somnolence, respiratory distress, and feeding difficulty; these effects have been self-limited in some cases but have required intensive care in others. Fenazine should be used during pregnancy only if the potential benefit to the mother clearly justifies the potential risk to the fetus, and only under close medical supervision.
Lactation: Fluphenazine is excreted into breast milk. Because of the potential for sedation and other adverse effects in the nursing infant, and because the drug's long-acting depot formulation prolongs infant exposure once the mother is dosed, breastfeeding during Fenazine therapy should be discussed with a physician, weighing the benefits of breastfeeding against the potential risk to the infant.
Precautions & Warnings
Boxed warning
Increased mortality in elderly patients with dementia-related psychosis: Elderly patients with dementia-related psychosis treated with antipsychotic drugs, including Fenazine, are at an increased risk of death compared with placebo, most commonly from cardiovascular or infectious (e.g., pneumonia) causes. Fenazine is not approved for the treatment of dementia-related psychosis.
Depot-specific counseling point
Because Fenazine is a long-acting injectable, any adverse reaction that occurs — including extrapyramidal symptoms, allergic/hypersensitivity reactions, or neuroleptic malignant syndrome — may take substantially longer to resolve than a reaction to an oral dose of fluphenazine, since the depot cannot be rapidly removed from the body once injected. Patients and caregivers should be counselled about this before the first injection.
Tardive dyskinesia
Prolonged use of Fenazine may lead to tardive dyskinesia, a syndrome of potentially irreversible, involuntary dyskinetic movements. Risk appears to increase with duration of treatment and total cumulative dose, and is highest in elderly patients, especially women, although it can occur (rarely) even after short-term treatment. There is no known reliable treatment for established tardive dyskinesia; the drug should be discontinued at the first sign, if clinically feasible.
Neuroleptic malignant syndrome (NMS)
A rare but potentially fatal reaction that can occur with any antipsychotic, including Fenazine. Signs include hyperthermia, severe muscle rigidity, altered consciousness, and autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, cardiac arrhythmia). Immediate discontinuation and intensive supportive treatment are required. Because of the depot formulation, recovery from NMS induced by Fenazine may take longer than with oral antipsychotics.
Other precautions
- QT prolongation: Use with caution in patients with cardiac disease, electrolyte disturbances, or concomitant QT-prolonging drugs.
- Seizure threshold: Fenazine may lower the seizure threshold; use with caution in patients with a seizure disorder or other predisposing factors.
- Orthostatic hypotension: may increase risk of falls, particularly in elderly or debilitated patients.
- Hepatic and hematologic monitoring: periodic liver function tests and complete blood counts are advisable, especially during the initial months of therapy.
- Heat exposure: Fenazine may impair the body's ability to reduce core temperature; avoid extreme heat exposure and strenuous activity in hot conditions.
- Driving/operating machinery: sedation and motor impairment may occur; caution patients accordingly.
- Alcohol: avoid concurrent use, as effects are potentiated.
Overdose Effects of Fenazine
Overdose with Fenazine is a medical emergency. Because it is a long-acting depot injection, toxic effects may develop and persist over an extended period compared with oral overdose, and cannot be rapidly terminated by drug removal.
Symptoms of overdose may include severe extrapyramidal reactions, deep sedation or coma, hypotension, agitation, seizures, hyperthermia or hypothermia, and cardiac arrhythmias (including QT prolongation).
If overdose is suspected, seek immediate emergency medical attention or contact a poison control center right away. Management is supportive and symptomatic, with continuous monitoring of vital signs, ECG, and airway/respiratory status, generally in a hospital setting; there is no specific antidote. Because of the prolonged depot effect, extended observation and monitoring are typically required.
Storage Conditions
Store at controlled room temperature, 20°C to 25°C (68°F to 77°F); brief excursions between 15°C and 30°C are permitted. Protect from light — keep the vial in its outer carton until use. Do not freeze. Keep out of reach of children.
Use In Special Populations
Pregnant women
Use Fenazine during pregnancy only if the potential benefit justifies the potential risk to the fetus. Monitor neonates exposed during the third trimester for extrapyramidal or withdrawal symptoms (see Pregnancy and Lactation).
Breastfeeding women
Fluphenazine passes into breast milk; discuss the risks and benefits of breastfeeding with a physician before using Fenazine while nursing.
Pediatric patients
Fenazine is not recommended for children under 12 years of age. Safety and efficacy in the pediatric population have not been established.
Elderly patients
Elderly patients, particularly women, have a higher risk of tardive dyskinesia and are generally more susceptible to hypotension, sedation, and anticholinergic effects. Fenazine carries a boxed warning against use in elderly patients with dementia-related psychosis due to increased risk of death, and is not approved for this indication. Use the lowest effective dose in this population.
Hepatic impairment
Fenazine is contraindicated in severe liver disease; use with caution and monitor liver function in any degree of hepatic impairment.
Renal impairment
No specific dose adjustment has been established; use with caution and monitor clinical response.
Duration Of Treatment
Fenazine is intended for long-term maintenance therapy of schizophrenia. There is no fixed treatment duration — therapy is typically continued for as long as maintenance antipsychotic treatment is clinically indicated, with the dose and injection interval (commonly every 2 to 4 weeks) individualised and periodically reassessed by the treating physician based on symptom control and tolerability. Any decision to discontinue or taper should be made by the prescribing physician, since therapeutic and adverse effects of a depot injection persist for weeks after the last dose.
Drug Classes
Phenothiazine antipsychotic (first-generation/typical antipsychotic), piperazine subgroup; long-acting depot injectable formulation.
Mode Of Action
Fluphenazine Decanoate exerts its antipsychotic effect primarily through post-synaptic blockade of dopamine D2 receptors in the mesolimbic/mesocortical pathways, reducing dopaminergic overactivity thought to underlie positive psychotic symptoms. It also has antagonist activity at alpha-1 adrenergic, histamine H1, and muscarinic cholinergic receptors, contributing to its side-effect profile. The decanoate ester formulation, delivered in an oily depot vehicle, is slowly hydrolysed to release free fluphenazine over an extended period, producing a long duration of action (roughly 2–4 weeks per injection) compared with oral fluphenazine.
Pediatric Uses
Fenazine is not recommended for children under 12 years of age. There is no adequate clinical experience with this drug in children, and its safety and efficacy in the pediatric population have not been established. If antipsychotic treatment is required in a child or adolescent, the prescribing physician will select an appropriate agent and monitor closely for extrapyramidal symptoms, sedation, and other adverse effects, which pediatric patients may be more sensitive to than adults.
Frequently Asked Questions
Q: What is Fenazine 25 mg/ml IM/SC Injection used for?
A: Fenazine 25 mg/ml IM/SC Injection is a long-acting injectable antipsychotic used for maintenance treatment of schizophrenia, especially in patients who have difficulty taking a daily oral antipsychotic. A single injection can control symptoms for up to 4 weeks or longer.
Q: How often is Fenazine 25 mg/ml IM/SC Injection given?
A: After an initial dose, Fenazine 25 mg/ml IM/SC Injection is usually given every 2 to 4 weeks by deep intramuscular or subcutaneous injection, with the exact dose and interval individualised by the treating physician based on response.
Q: What are the main side effects of Fenazine 25 mg/ml IM/SC Injection?
A: Common side effects of Fenazine 25 mg/ml IM/SC Injection include drowsiness, dry mouth, constipation, blurred vision, and extrapyramidal symptoms such as tremor, muscle stiffness, and restlessness. Less common but serious risks include tardive dyskinesia (potentially irreversible involuntary movements) and neuroleptic malignant syndrome (a rare, life-threatening reaction with high fever, muscle rigidity, and confusion), which requires immediate medical attention.
Q: Is Fenazine 25 mg/ml IM/SC Injection safe in pregnancy?
A: Fenazine 25 mg/ml IM/SC Injection should be used in pregnancy only if the potential benefit to the mother clearly outweighs the potential risk to the fetus. Babies exposed in the third trimester may show withdrawal or extrapyramidal symptoms after birth, such as agitation, tremor, or feeding difficulty. Always consult a physician before use during pregnancy.
Q: Can Fenazine 25 mg/ml IM/SC Injection be stopped immediately if side effects occur?
A: No. Because Fenazine 25 mg/ml IM/SC Injection is a long-acting depot injection, it cannot be removed from the body once given, so any side effect — including allergic reactions or extrapyramidal symptoms — may take much longer to resolve than with an oral dose. Contact a physician promptly if troubling symptoms occur; do not wait for the next scheduled dose.
Q: Why does Fenazine 25 mg/ml IM/SC Injection carry a boxed warning for elderly patients?
A: Elderly patients with dementia-related psychosis who are treated with antipsychotic drugs, including Fenazine 25 mg/ml IM/SC Injection, have a higher risk of death, mainly from cardiovascular or infectious causes. Because of this, Fenazine 25 mg/ml IM/SC Injection is not approved for treating dementia-related psychosis in elderly patients.
Disclaimer
The information provided is accurate to the best of our knowledge, but it does not replace professional medical advice. We cannot guarantee its completeness or accuracy, and the absence of specific information about a drug should not be taken as an endorsement. We are not responsible for any consequences arising from this information, so please consult a healthcare professional for any concerns or questions.
