
8% Off
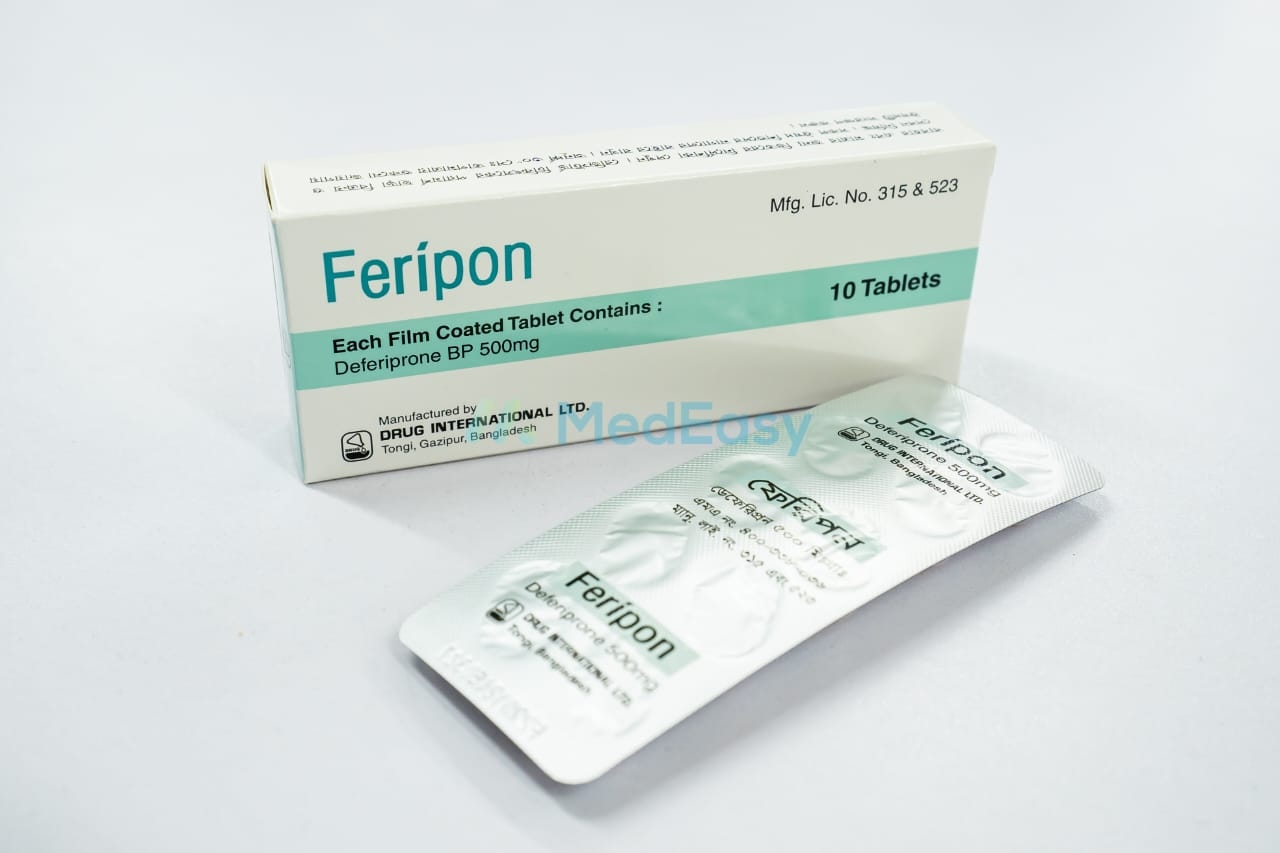
Feripon500 mg
Drug International Ltd.
৳165.60
Add to cart


Defera is an oral iron chelator used to reduce chronic iron overload.
The safety and efficacy of Defera have not been established for iron overload due to myelodysplastic syndrome or Diamond-Blackfan anemia, and it should not be used for these conditions outside of a specialist/clinical-trial setting.
Defera is generally reserved as second-line therapy and, in some regimens, is used in combination with deferoxamine under specialist supervision for patients with severe iron overload.
Each film-coated tablet contains Deferiprone INN 500 mg (also available as 1000 mg tablets and as an oral solution 100 mg/mL in some markets, depending on manufacturer). Excipients vary by brand and formulation.
Defera is a synthetic, orally active, bidentate iron-chelating agent belonging to the hydroxypyridinone class. It is used to remove excess iron from the body in patients who require long-term blood transfusions (for example, in thalassemia major), where transfusions lead to progressive accumulation of iron that can damage the heart, liver, and endocrine glands if untreated.
Defera carries a boxed warning for agranulocytosis, a potentially fatal drop in white blood cells, and requires mandatory regular blood count monitoring throughout treatment.
Iron-chelating agent (antidote for iron overload); hydroxypyridinone class
Deferiprone is a bidentate ligand; three molecules of Deferiprone surround one iron(III) atom (3:1 stoichiometry) to form a stable, neutral complex that is excreted mainly in the urine, with a small amount eliminated in feces. This removes excess iron from tissues and reduces harmful labile iron that would otherwise catalyze free-radical damage.
| Indication | Starting dose | Maximum dose |
|---|---|---|
| Transfusional iron overload (thalassemia syndromes, sickle cell disease, other anemias) | 75 mg/kg/day given in divided doses (twice or three times daily depending on formulation) | 99 mg/kg/day |
Dose is individualized and adjusted based on serum ferritin trends and clinical response. In some national labels (including Bangladesh), Defera is dosed as 25 mg/kg three times daily (75 mg/kg/day) in patients above 6 years of age, up to a maximum of 100 mg/kg/day, when deferoxamine therapy is inadequate or contraindicated; the treating physician's local label and monitoring protocol should be followed.
Dedicated dose-adjustment studies are lacking. Defera should be used with caution and close monitoring in patients with hepatic impairment (see Precautions) and is not recommended in patients with significant renal impairment unless benefit clearly outweighs risk, under specialist supervision.
Defera tablets are usually taken with meals to reduce gastrointestinal upset, swallowed whole with water; the oral solution (where available) should be measured with the supplied dosing device. Doses should be spaced evenly through the day. Do not take iron- or mineral-containing supplements (e.g., antacids, zinc, or iron products) within 4 hours of a dose (see Interactions).
Take Defera by mouth, generally with food, at evenly spaced intervals as prescribed. Swallow tablets whole; use the dosing device provided for oral solution formulations. Do not stop or change the dose without consulting the treating physician, since ongoing blood count monitoring is required throughout treatment.
See Precautions and Warnings for the mandatory blood-count monitoring required even outside these absolute contraindications.
In patients treated for sickle cell disease or other anemias, fever, bone/back pain, sickle cell crisis, sore throat, and upper respiratory infection have also been reported with Defera.
Defera has shown embryo-fetal harm (fetal loss and malformations) in animal studies at clinically relevant doses, and human data are insufficient to rule out risk; treatment should generally be avoided in pregnancy. Defera should be used during pregnancy only if clearly needed and the potential benefit justifies the potential risk to the fetus, and only under direct physician supervision. Women of reproductive potential should use effective contraception during treatment with Defera and for a period after stopping (per treating physician's advice); male patients are advised to use contraception for a period after stopping treatment.
It is not known whether Defera passes into human breast milk. Breastfeeding is generally not recommended during treatment with Defera and for a period after the last dose; a physician should be consulted before breastfeeding.
Defera can cause agranulocytosis that can lead to serious infection and death; neutropenia may precede agranulocytosis. Absolute neutrophil count (ANC) must be measured before starting Defera and monitored on a mandatory regular schedule (typically weekly) throughout treatment. Patients must be instructed to report any signs or symptoms of infection (fever, sore throat, mouth sores, chills) immediately. Treatment with Defera must be interrupted if neutropenia is confirmed and stopped if agranulocytosis occurs.
Limited data on overdose with Defera are available; neurological symptoms (such as unsteady gait/cerebellar signs, double vision, and slowed movement) have been reported at doses roughly 2.5-3 times the recommended dose, with gradual recovery after stopping. There is no specific antidote for Defera overdose. In case of suspected overdose, seek immediate medical attention or contact emergency services/poison control; treatment is supportive and symptomatic under medical supervision.
Store Defera at room temperature (20-25°C / 68-77°F), with excursions permitted to 15-30°C; protect from moisture and light, and keep the container tightly closed. Keep out of reach of children.
Data are limited; use Defera with caution and close monitoring in patients with significant renal impairment.
Use Defera with caution and enhanced liver-function monitoring in patients with hepatic impairment, given the risk of transaminase elevation and rare hepatic fibrosis (see Precautions).
Clinical experience with Defera in elderly patients is limited, as chronic transfusional iron overload predominantly affects younger patients; use with routine monitoring if prescribed.
See Pediatric Uses.
Treatment with Defera is typically long-term/chronic, continuing for as long as transfusion-related iron overload persists. The treating physician periodically reassesses the need for continued therapy using serum ferritin trends and, where available, organ (cardiac/hepatic) iron measurements, adjusting or stopping Defera as clinically indicated.
Deferiprone belongs to the class of iron-chelating agents (hydroxypyridinone chelators), used as antidotes for chronic iron overload.
Deferiprone is a bidentate iron chelator: three molecules of Deferiprone bind one atom of trivalent iron to form a stable, water-soluble complex that is then excreted, principally in the urine. By binding free and loosely-bound (labile) iron, Deferiprone reduces iron-catalyzed oxidative tissue damage and lowers total body iron burden over time.
The safety and effectiveness of Defera have been established in pediatric patients 8 years of age and older for transfusional iron overload, using the same weight-based dosing as adults (see Dosage and Administration). Some national labels (including in Bangladesh) permit use from 6 years of age when deferoxamine therapy is inadequate or contraindicated, under specialist supervision. Safety and effectiveness of Defera in children younger than the locally approved minimum age have not been established, and mandatory neutrophil monitoring applies equally to pediatric patients.
Q: What is Defera 500 mg Tablet used for?
A: Defera 500 mg Tablet is used to remove excess iron from the body in patients with chronic transfusional iron overload, most commonly due to thalassemia major, when other chelation therapy is inadequate or not tolerated.
Q: Why do I need regular blood tests while taking Defera 500 mg Tablet?
A: Defera 500 mg Tablet carries a risk of agranulocytosis, a serious and potentially fatal drop in a type of white blood cell that fights infection. Regular absolute neutrophil count (blood) tests, typically weekly, are mandatory throughout treatment so that the medicine can be stopped promptly if your counts fall.
Q: What should I do if I get a fever or sore throat while on Defera 500 mg Tablet?
A: Contact your doctor immediately and have a blood count checked, since fever, sore throat, or mouth sores can be early signs of a serious drop in white blood cells associated with Defera 500 mg Tablet. Do not wait for your next scheduled test.
Q: Can Defera 500 mg Tablet be used during pregnancy?
A: Defera 500 mg Tablet can harm a developing fetus and should generally be avoided in pregnancy; it should only be used if clearly necessary and the benefit outweighs the risk, under close physician supervision, and effective contraception is recommended during treatment.
Q: Is it normal for my urine to change color on Defera 500 mg Tablet?
A: Yes, a reddish-brown discoloration of urine is a common and harmless effect of Defera 500 mg Tablet, reflecting the excretion of the iron-chelator complex; it does not indicate a problem on its own.
Q: Can I take iron or zinc supplements with Defera 500 mg Tablet?
A: Iron-, aluminum-, or zinc-containing antacids or supplements can bind to Defera 500 mg Tablet and reduce its absorption, so these should be separated from Defera 500 mg Tablet doses by at least 4 hours, and any supplementation should be guided by your physician based on your monitored zinc and iron levels.
Disclaimer
The information provided is accurate to the best of our knowledge, but it does not replace professional medical advice. We cannot guarantee its completeness or accuracy, and the absence of specific information about a drug should not be taken as an endorsement. We are not responsible for any consequences arising from this information, so please consult a healthcare professional for any concerns or questions.
