
10% Off
Cosium10 mg
ACME Laboratories Ltd.
৳45.00
Add to cart
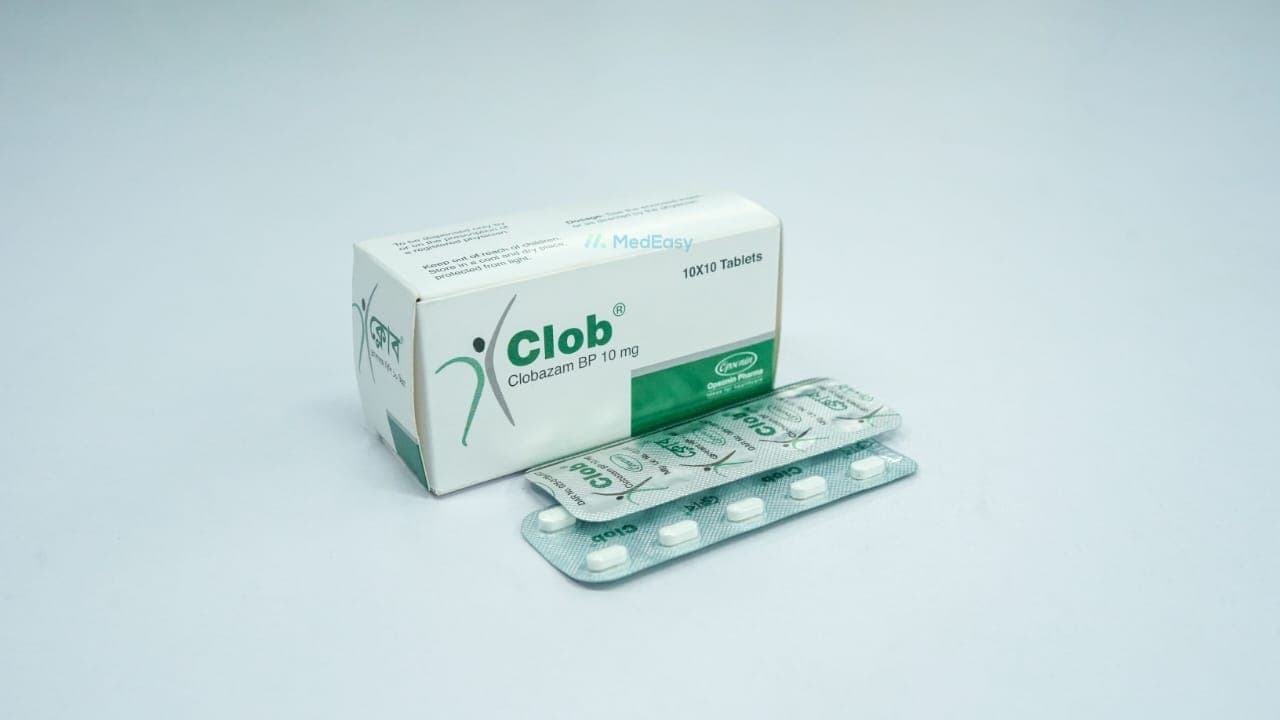

Clob is a benzodiazepine anticonvulsant used in the management of seizure disorders and, in some markets, anxiety. Its indications are classified below by strength of evidence.
The exact approved indications, dosage forms and prescribing status of Clob can vary by country; a physician should confirm the appropriate use for an individual patient.
Each Clobazam tablet contains Clobazam Ph.Eur./USP as the active ingredient, commonly available in strengths such as 5 mg, 10 mg and 20 mg. Clobazam is also formulated as an oral suspension (2.5 mg/mL) in some markets for patients who cannot swallow tablets. Tablets additionally contain standard pharmaceutical excipients (e.g., lactose, microcrystalline cellulose, magnesium stearate) used for tablet formation; the exact excipient list may vary by manufacturer and should be confirmed on the product label.
Clob is a 1,5-benzodiazepine, chemically and pharmacologically distinct from the more commonly used 1,4-benzodiazepines (such as diazepam or clonazepam), though it shares the same broad class effects of enhancing inhibitory neurotransmission in the central nervous system. Clob is used mainly as an add-on (adjunctive) anticonvulsant for difficult-to-control seizure disorders, most notably Lennox-Gastaut syndrome, and in some countries as a short-term anxiolytic.
Clob and its major active metabolite, N-desmethylClob, both contribute to its clinical effect. Clob is a Schedule IV controlled substance in the United States because of its potential for abuse, misuse and physical dependence, and it should only be used under medical supervision, exactly as prescribed.
Clob belongs to the benzodiazepine class of medicines, specifically the 1,5-benzodiazepine subgroup. Functionally it is classified as an anticonvulsant (antiepileptic) / anxiolytic agent.
Clobazam acts by binding to the benzodiazepine recognition site on the gamma-aminobutyric acid type A (GABA-A) receptor complex in the central nervous system. This binding enhances the affinity of GABA, the brain's principal inhibitory neurotransmitter, for its receptor, which increases the frequency of chloride-channel opening. The resulting increase in chloride ion influx hyperpolarises the neuronal membrane, reducing neuronal excitability and raising the seizure threshold, and also producing anxiolytic and sedative effects.
Clobazam is metabolised in the liver, principally via CYP3A4 (and to a lesser extent CYP2C19), to its major active metabolite, N-desmethylclobazam, which is itself further metabolised primarily by CYP2C19. This active metabolite contributes substantially to the overall clinical (anticonvulsant) effect and has a longer half-life than the parent drug, which is relevant for dosing in patients who are CYP2C19 poor metabolisers (see Use in Special Populations).
Clob dosing must always be individualised by a physician and titrated gradually. Below is a general summary; the prescriber's instructions should always take precedence.
| Population | Starting Dose | Titration | Usual Maintenance / Maximum Dose |
|---|---|---|---|
| Adults and children >30 kg | 10 mg/day (in 1-2 divided doses) | Increase by 10 mg/day at weekly intervals as tolerated | Up to 40 mg/day |
| Children 2 years and older, ≤30 kg | 5 mg/day | Increase by 5 mg/day at weekly intervals as tolerated | Up to 20 mg/day |
| Elderly patients | 5 mg/day | Titrate more slowly | Generally half of standard adult doses above, unless well tolerated |
Total daily doses above 5 mg are usually given in two divided doses per day. Doses may be titrated further only under continued physician supervision.
Where Clob is licensed for anxiety, a typical adult starting dose is low (e.g., 10-20 mg/day in divided doses), for the shortest duration necessary (generally no more than 2-4 weeks including tapering), based on physician assessment.
Clob must never be stopped abruptly after regular use; the physician will taper the dose gradually (e.g., reducing the total daily dose by roughly 5-10 mg per week) to reduce the risk of withdrawal symptoms and, in patients with epilepsy, rebound seizures (see Precautions and Warnings).
Clob tablets are taken by mouth, with or without food, generally in one or two divided doses per day as directed. Tablets may be swallowed whole, broken in half along the score line, or crushed and mixed with a small amount of soft food (such as applesauce) immediately before use if a patient has difficulty swallowing; any oral suspension formulation should be shaken well and measured with the calibrated oral syringe/device provided.
Clob should be taken exactly as prescribed, at the same time(s) each day. Patients must not increase the dose, take extra doses, or stop Clob suddenly without consulting their physician, because of the risk of withdrawal and, in epilepsy, rebound seizures.
Clob has several clinically significant drug interactions that should be reviewed by a physician or pharmacist before co-prescribing.
Patients should inform their physician of all prescription drugs, over-the-counter medicines, and herbal products they are taking before starting Clob.
Clobazam is contraindicated in patients with a known history of hypersensitivity to Clobazam or to any component of the formulation.
As with all benzodiazepines, side effects of Clob are generally dose-related and most prominent when starting treatment or after a dose increase.
Patients should seek prompt medical attention for any rash, unexplained fever, blistering/peeling skin, difficulty breathing, or thoughts of self-harm while taking Clob.
Pregnancy: Data on Clob use in human pregnancy are limited. Animal studies have shown evidence of embryo-fetal toxicity at exposures below those used clinically in humans. Like other benzodiazepines, Clob used late in pregnancy may cause sedation ("floppy infant") or withdrawal symptoms in the newborn. Clob should be used during pregnancy only if the potential benefit to the mother clearly justifies the potential risk to the fetus, and only under close physician supervision; it should not be stopped abruptly without medical advice. Women who become pregnant while taking Clob should consult their physician promptly and, where available, consider enrolling in an antiepileptic drug pregnancy registry.
Lactation: Clob and its active metabolite are excreted into breast milk. Breastfed infants of mothers taking Clob should be monitored for excess sedation, poor feeding, and inadequate weight gain. Breastfeeding while using Clob should only be undertaken after discussion with a physician, weighing the benefits of breastfeeding against the potential risk to the infant.
Clob carries several important warnings that patients and caregivers should understand.
Even when taken as prescribed, Clob can cause physical and psychological dependence and carries a risk of abuse, misuse and addiction, which can lead to overdose or death. A physician will assess each patient's risk before prescribing and will monitor for signs of misuse during treatment.
Combining Clob with opioids or other central nervous system (CNS) depressants (including alcohol) can cause profound sedation, respiratory depression, coma and death. Such combinations should only be used when there is no adequate alternative, at the lowest effective doses (see Interactions).
After regular use, particularly at higher doses or for a prolonged period, stopping Clob suddenly or reducing the dose too quickly can precipitate a serious, potentially life-threatening withdrawal reaction, including seizures (even in patients without epilepsy), tremor, anxiety, agitation, and psychiatric symptoms. Clob must always be discontinued gradually, under a physician's guidance.
Clob has been specifically associated with serious, and rarely fatal, skin reactions — Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN) — a risk that several regulatory agencies highlight with particular prominence for Clob compared with many other antiseizure medicines. Treatment should be stopped immediately, and medical attention sought, at the first sign of a rash, blistering, mucosal lesions, or skin peeling, unless the cause is clearly unrelated to Clob.
Antiepileptic drugs as a class, including Clob, are associated with a small increased risk of suicidal thoughts or behaviour. Patients and caregivers should watch for new or worsening depression, unusual changes in mood or behaviour, or thoughts of self-harm, and report these to a physician immediately.
Clob commonly causes somnolence and can impair alertness, coordination and reaction time. Patients should avoid driving, operating heavy machinery, or performing other hazardous tasks until they know how Clob affects them.
Elderly patients are more sensitive to the sedative and motor-impairing effects of Clob and are at increased risk of falls, confusion and excessive sedation; lower doses and slower titration are used in this group (see Use in Special Populations).
Overdose of Clob, especially when combined with alcohol or other CNS depressants, can be life-threatening. Symptoms may range from marked drowsiness, confusion, slurred speech, impaired coordination (ataxia) and low muscle tone, through to severe respiratory depression and coma.
Clob overdose is a medical emergency. If overdose is suspected, seek immediate emergency medical attention or contact a poison control centre right away; do not wait for symptoms to appear. Do not attempt to treat an overdose at home. Management in a medical facility is generally supportive (securing the airway, monitoring breathing and circulation); a specific benzodiazepine-reversal agent may be used by medical professionals in certain circumstances, but its use carries its own risks (including seizures in some patients) and must only be given by trained clinical staff.
Store at room temperature (below 30°C), away from light and moisture. Keep out of reach of children.
Safety and efficacy of Clob for Lennox-Gastaut syndrome have been established in children 2 years of age and older, with weight-based dosing as described under Dosage and Administration. Safety and efficacy in children younger than 2 years have not been established, and Clob should not be used in this age group outside specialist guidance.
Elderly patients generally clear Clob more slowly and are more sensitive to its sedative effects. A lower starting dose (typically 5 mg/day) with slower, careful titration is recommended, with close monitoring for excess sedation, confusion and falls.
No dosage adjustment is generally required in mild-to-moderate renal impairment. Data in severe renal impairment are limited, and Clob should be used with caution and close monitoring in this group.
In mild-to-moderate hepatic impairment, a lower starting dose (e.g., 5 mg/day) with slower titration is recommended. Data in severe hepatic impairment are insufficient; Clob should be used with particular caution, if at all, and only under specialist supervision.
Patients who are genetically poor metabolisers of CYP2C19 accumulate substantially higher levels of Clob's active metabolite. A lower starting dose with slower titration is recommended in this group; genetic testing may inform dosing where available.
The duration of Clob therapy is individualised by the treating physician. When used as adjunctive therapy for Lennox-Gastaut syndrome, Clob is typically continued long-term, with periodic reassessment of continued need and benefit. When used for short-term anxiety (in markets where licensed), treatment is generally limited to the shortest period necessary, usually no more than 2-4 weeks including any tapering period, because of the risk of tolerance, dependence and withdrawal with longer use. Clob should never be continued or discontinued without a physician's guidance.
Clobazam belongs to the following drug classes: Benzodiazepines (1,5-benzodiazepine subgroup); Anticonvulsants / Antiepileptic drugs (AEDs); Anxiolytics; and, in the United States, a Schedule IV controlled substance.
Clobazam works by binding to the benzodiazepine site on GABA-A receptors in the brain, enhancing the inhibitory action of the neurotransmitter GABA. This increases chloride ion flow into neurons, making them less excitable, which raises the seizure threshold (anticonvulsant effect) and produces calming, anxiolytic and sedative effects. Its active metabolite, N-desmethylclobazam, contributes substantially and often more durably to this effect than the parent compound (see Pharmacology for full mechanistic and metabolic detail).
Clob is approved for adjunctive treatment of seizures associated with Lennox-Gastaut syndrome in children 2 years of age and older, using weight-based dosing (see Dosage and Administration). Safety and effectiveness in children younger than 2 years have not been established. In pediatric patients, Clob has been associated with drooling, behavioural changes (including aggression), and sedation; caregivers should monitor closely, especially at treatment initiation and after dose changes. As with adults, Clob should never be stopped abruptly in children without medical guidance because of withdrawal and rebound-seizure risk.
Q: What is Clob 10 mg Tablet used for?
A: Clob 10 mg Tablet is a benzodiazepine medicine used mainly as an add-on treatment for seizures in Lennox-Gastaut syndrome, a severe childhood-onset epilepsy syndrome, in patients 2 years of age and older. In some countries it is also used for short-term relief of severe anxiety. Clob 10 mg Tablet is always used alongside other treatments as directed by a physician, not as a first-choice stand-alone medicine.
Q: Can I stop taking Clob 10 mg Tablet suddenly if I feel better?
A: No. You must never stop Clob 10 mg Tablet suddenly or reduce the dose on your own. Stopping Clob 10 mg Tablet abruptly after regular use can cause a serious, potentially life-threatening withdrawal reaction, including seizures (even if you do not otherwise have epilepsy), agitation, and other symptoms. Your physician will reduce the dose gradually over time if treatment needs to stop.
Q: Is it safe to take Clob 10 mg Tablet with alcohol or opioid painkillers?
A: No. Combining Clob 10 mg Tablet with alcohol, opioids, or other medicines that slow down the central nervous system can cause profound sedation, dangerously slowed or stopped breathing, coma, and death. Always tell your physician about every medicine, supplement, and alcohol use before and during Clob 10 mg Tablet treatment.
Q: What skin symptoms should make me stop Clob 10 mg Tablet and seek medical help?
A: Clob 10 mg Tablet has been linked to rare but serious skin reactions, including Stevens-Johnson syndrome and toxic epidermal necrolysis. If you develop a new rash, blistering, peeling skin, mouth or eye sores, or fever with a rash while taking Clob 10 mg Tablet, stop the medicine and seek immediate medical attention, unless your physician has confirmed the symptom is clearly unrelated.
Q: Can Clob 10 mg Tablet be used during pregnancy or breastfeeding?
A: Clob 10 mg Tablet should be used in pregnancy only if the potential benefit clearly outweighs the potential risk to the baby, as benzodiazepines used late in pregnancy can cause sedation or withdrawal symptoms in the newborn; this decision should always be made together with a physician. Clob 10 mg Tablet also passes into breast milk and can sedate a breastfed infant, so breastfeeding while taking Clob 10 mg Tablet should only be done under medical advice, with the infant monitored for excess drowsiness or poor feeding.
Q: Is Clob 10 mg Tablet addictive?
A: Yes, Clob 10 mg Tablet carries a recognised risk of abuse, misuse, physical dependence and addiction, even when taken exactly as prescribed. It should be used only for as long as your physician recommends, at the prescribed dose, and never shared with anyone else.
Disclaimer
The information provided is accurate to the best of our knowledge, but it does not replace professional medical advice. We cannot guarantee its completeness or accuracy, and the absence of specific information about a drug should not be taken as an endorsement. We are not responsible for any consequences arising from this information, so please consult a healthcare professional for any concerns or questions.

