
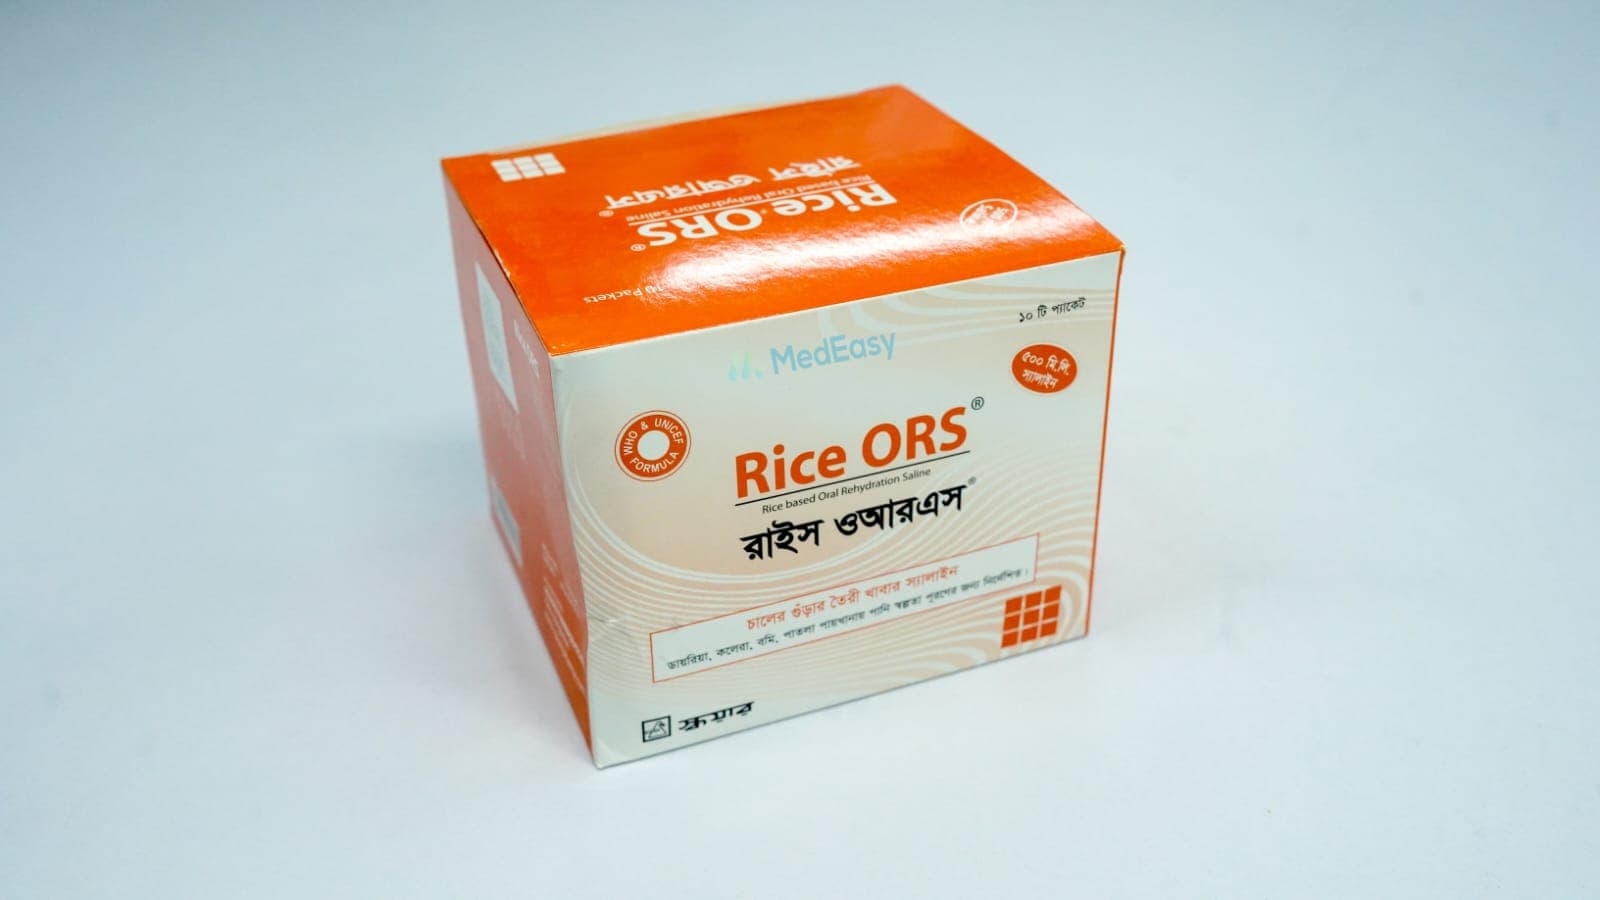

Medicine overview
Indications of Rice ORS
Established Uses
Rice ORS is indicated for the prevention and treatment of dehydration and associated electrolyte losses caused by diarrhea of any cause (including acute gastroenteritis and cholera) in infants, children, and adults. It is used as first-line oral fluid and electrolyte replacement therapy in mild to moderate dehydration.
Guideline-Supported Use
Rice ORS is recommended by WHO/UNICEF diarrheal disease management protocols as part of Plan A (home management to prevent dehydration) and Plan B (treatment of some dehydration), used together with continued feeding and zinc supplementation in children.
Adjunct Use
In cholera and other severe secretory diarrheas, Rice ORS is used as an adjunct alongside appropriate antimicrobial therapy (when indicated) and, in cases of severe dehydration, following initial intravenous fluid resuscitation, to complete rehydration and replace ongoing stool losses.
Rice ORS does not treat the underlying cause of diarrhea (e.g., infection); it corrects and prevents fluid and electrolyte depletion resulting from it.
Composition
Rice Based Oral Rehydration Saline is an oral rehydration salt formulation in which rice-derived carbohydrate (rice starch/rice syrup solids) replaces glucose as the carbohydrate source. Each sachet, when reconstituted with the specified volume of clean drinking water, provides a balanced solution of electrolytes and carbohydrate, typically including sodium chloride, potassium chloride, and an alkalinizing agent (such as trisodium citrate), together with rice-derived carbohydrate.
Exact electrolyte and carbohydrate content per sachet can vary by manufacturer; the reconstituted osmolarity is formulated to approximate WHO-recommended low-osmolarity oral rehydration solution standards.
Description
Rice ORS is an oral rehydration solution (ORS) in which the carbohydrate component is derived from rice (rice starch or rice syrup solids) rather than glucose. It is supplied as a powder for reconstitution with water and is used to replace fluid and electrolytes lost through diarrhea and vomiting.
Rice-based formulations work on the same sodium-glucose cotransport principle as standard glucose-based ORS, but the complex rice carbohydrate is broken down gradually by intestinal amylase, releasing glucose more slowly. Some clinical studies, particularly in cholera, have shown modestly reduced stool output and shorter duration of diarrhea with rice-based ORS compared to standard glucose-based ORS, although both are effective and WHO-recommended options for rehydration.
Rice ORS is not an antibiotic and does not treat infections; it is a supportive fluid and electrolyte replacement therapy.
Therapeutic Class
Rice ORS belongs to the therapeutic class of Oral Rehydration Salts (ORS) / fluid and electrolyte replacement agents.
Pharmacology
Mechanism of Action
Rice Based Oral Rehydration Saline works through the sodium-glucose cotransport mechanism in the small intestinal brush border. Sodium is actively absorbed across the intestinal epithelium coupled with glucose (released from digestion of the rice-derived carbohydrate), and this co-transport drives passive absorption of water and other electrolytes (potassium, chloride), even when the intestinal secretory processes of diarrhea are still active.
The citrate (or bicarbonate) component helps correct the metabolic acidosis commonly associated with diarrheal fluid loss. Because rice starch is a complex carbohydrate digested progressively by intestinal amylases, glucose is released gradually, which may reduce stool osmotic load and, in some studies, stool output compared with standard glucose-based ORS.
Dosage & Administration of Rice ORS
General Principles
Rice ORS powder must be reconstituted with the exact volume of clean, safe drinking water specified on the sachet/pack before use — never with milk, soup, or other fluids, and never with less or more water than instructed. Give the solution orally, in frequent small sips or by spoon (or, for infants, a clean cup and spoon); avoid feeding bottles.
| Situation | Approximate Dosing |
|---|---|
| No visible dehydration (prevention, Plan A) | Children <2 years: 50–100 mL after each loose stool; children 2–10 years: 100–200 mL after each loose stool; ≥10 years and adults: as much as wanted, at least 200-300 mL after each loose stool. |
| Some dehydration (Plan B) | Approximately 75 mL/kg body weight given over the first 4 hours, reassessing hydration status regularly; continue with Plan A quantities once rehydrated. |
| Ongoing losses | Replace each further episode of vomiting or loose stool with an additional dose of Rice ORS as above. |
For severe dehydration, intravenous fluids are required first (see Contraindications); Rice ORS is then used to complete rehydration and maintain hydration once the patient can tolerate oral intake.
Continue offering usual food/breastfeeding/age-appropriate feeds alongside Rice ORS; do not withhold food.
Administration of Rice ORS
Wash hands before preparing Rice ORS. Dissolve the entire contents of one sachet in the exact volume of boiled-and-cooled or otherwise safe drinking water stated on the pack label (commonly 200 mL, 500 mL, or 1 litre depending on product size); stir until fully dissolved. Do not add sugar, salt, or other substances to the solution.
Give the prepared solution by mouth in small, frequent sips using a clean cup and spoon, especially in infants and young children who cannot drink from a cup safely. If the person vomits, wait 10 minutes and then resume giving Rice ORS more slowly.
Freshly reconstituted Rice ORS solution not consumed within 24 hours must be discarded and a fresh batch prepared.
Interaction of Rice ORS
Rice ORS itself is not systemically absorbed as a drug and has few clinically significant pharmacokinetic drug interactions. However, because it alters gastrointestinal fluid and electrolyte status, the following points are clinically relevant:
- Concomitant use with other sources of added sodium or potassium (e.g., potassium-sparing diuretics, potassium supplements, ACE inhibitors/ARBs) may increase the risk of hyperkalemia or hypernatremia; monitor electrolytes when used together in patients on such therapy.
- Oral medications taken at the same time as large volumes of Rice ORS may have altered absorption due to increased gastrointestinal transit/fluid; where practical, space other oral medicines from Rice ORS administration.
Contraindications
Rice Based Oral Rehydration Saline is contraindicated in:
- Severe dehydration or hypovolemic shock, where urgent intravenous fluid resuscitation is required rather than oral rehydration alone.
- Persistent vomiting that prevents any oral intake from being retained.
- Paralytic ileus or intestinal obstruction.
- Anuria or complete inability to pass urine.
In these situations, Rice Based Oral Rehydration Saline must not be used as a substitute for the required intravenous or other emergency treatment; it can be resumed once the underlying emergency is controlled and the patient is able to tolerate oral fluids.
Side Effects of Rice ORS
Rice ORS is generally very well tolerated when reconstituted and administered correctly. Reported effects are uncommon and usually related to incorrect preparation or administration rate:
- Vomiting, if the solution is given too quickly, especially in a dehydrated or nauseated patient.
- Abdominal distension or bloating.
- Hypernatremia or hyponatremia, and other electrolyte disturbances, if the solution is prepared with too little or too much water, respectively, or given in excessive amounts to a patient with impaired renal function (see Overdose Effects and Precautions).
Pregnancy & Lactation
Rice ORS is considered safe for use during pregnancy and breastfeeding when reconstituted and dosed correctly; oral rehydration therapy is a standard, recommended part of managing dehydration due to diarrhea or hyperemesis in pregnant and lactating women. As with any medicinal or supplemental product, a pregnant or breastfeeding woman with diarrhea or dehydration should consult a physician, particularly if symptoms are severe, prolonged, or associated with other warning signs, so that the underlying cause can also be assessed and treated.
Precautions & Warnings
- Always reconstitute Rice ORS with the exact volume of clean, safe drinking water specified on the pack; a solution that is too concentrated can be harmful (risk of hypernatremia), especially in infants, while one that is too dilute may not adequately replace electrolyte losses.
- Do not add sugar, salt, or other ingredients to the prepared solution.
- Seek prompt medical attention if there are signs of severe dehydration (lethargy or unconsciousness, sunken eyes, very little or no urine output, inability to drink or keep fluids down, skin that stays pinched when pinched), blood in the stool, high fever, or diarrhea lasting more than a few days — especially in infants, young children, and the elderly.
- Use caution and seek medical advice in patients with significant renal impairment or conditions predisposing to electrolyte imbalance, as such patients are at higher risk of hyperkalemia, hypernatremia, or fluid overload with rehydration therapy (see Use in Special Populations).
- Discard any reconstituted Rice ORS solution not used within 24 hours; prepare a fresh solution.
- Rice ORS treats dehydration and electrolyte loss but does not treat the underlying cause of diarrhea (e.g., a bacterial or parasitic infection); seek medical evaluation if a specific cause needs to be identified and treated (see Contraindications for when it should not be used).
Overdose Effects of Rice ORS
Excessive or overly concentrated intake of Rice ORS, particularly in infants, young children, or patients with impaired kidney function, can lead to electrolyte disturbances such as hypernatremia, hyperkalemia, or fluid overload, which may present as irritability, weakness, muscle twitching, seizures, or swelling.
If overdose or incorrect concentration is suspected, or if any concerning symptoms develop after taking Rice ORS, stop administration and seek immediate medical attention or contact a poison control center; do not attempt specific home treatment for suspected electrolyte overdose.
Storage Conditions
Store Rice ORS sachets/powder at room temperature (below 30°C), in a dry place away from light and moisture. Keep out of reach of children. Once reconstituted, use the solution within 24 hours and discard any unused portion thereafter; do not refrigerate for extended storage or reuse leftover solution the next day.
Use In Special Populations
- Infants (including neonates): Rice ORS is appropriate for use in infants, including newborns, using age-appropriate volumes and administration by cup/spoon rather than a bottle; severe dehydration in this age group requires urgent medical care and may need intravenous fluids first.
- Elderly: No specific dose adjustment is required, but elderly patients, especially those with renal or cardiac impairment, should be monitored for fluid overload or electrolyte disturbance during rehydration.
- Renal impairment: Use with caution and under medical supervision, as impaired potassium and sodium excretion increases the risk of hyperkalemia and hypernatremia with Rice ORS.
- Hepatic impairment: No specific dose adjustment is established; use as clinically indicated.
Duration Of Treatment
Rice ORS should be continued for as long as diarrhea and/or vomiting persist, replacing ongoing fluid losses after each loose stool or vomiting episode, and continued for 24 hours after diarrhea stops or as advised by a physician. If diarrhea persists beyond a few days, or dehydration signs worsen despite use of Rice ORS, medical evaluation should be sought promptly.
Reconstitution
Rice ORS is supplied as a powder that must be reconstituted before use. Empty the entire contents of one sachet into a clean container and add the exact volume of cool, previously boiled (or otherwise safe/clean) drinking water indicated on the product label (commonly 200 mL, 500 mL, or 1 litre, depending on pack size). Stir or shake until the powder is fully dissolved. Do not use hot water, milk, soup, fruit juice, or carbonated drinks to reconstitute Rice ORS, and do not add extra sugar or salt. Prepare a fresh solution at least once every 24 hours and discard any solution older than 24 hours.
Drug Classes
Rice Based Oral Rehydration Saline is classified under Oral Rehydration Salts (ORS), within the broader category of fluid, electrolyte, and acid-base replacement products.
Mode Of Action
Rice Based Oral Rehydration Saline restores fluid and electrolyte balance via intestinal sodium-glucose cotransport: sodium absorption is coupled to absorption of glucose released from digestion of the rice-derived carbohydrate, and this active transport process osmotically drives water absorption along with it, together with potassium and chloride, even during active secretory diarrhea. The citrate component helps buffer the metabolic acidosis that accompanies significant diarrheal losses.
Pediatric Uses
Rice ORS is a first-line, WHO-recommended therapy for prevention and treatment of dehydration due to diarrhea in infants and children of all ages, including neonates, and is considered a cornerstone of safe pediatric diarrheal disease management. Dosing is based on age and body weight (see Dosage and Administration/Dosage tables); administration by clean cup and spoon (not a feeding bottle) is recommended, with frequent small amounts, especially in infants. Breastfeeding and usual age-appropriate feeding should be continued alongside Rice ORS and not withheld. Caregivers should seek urgent medical care for infants and young children showing signs of severe dehydration, persistent vomiting, blood in stool, high fever, or diarrhea lasting more than a few days, as these children may require professional assessment and, in some cases, intravenous fluids in addition to or instead of Rice ORS.
Frequently Asked Questions
Q: What is Rice ORS 500 ml Saline used for?
A: Rice ORS 500 ml Saline is used to prevent and treat dehydration and replace lost electrolytes caused by diarrhea (including cholera and acute gastroenteritis) and vomiting, in both children and adults. It is a rice-carbohydrate-based oral rehydration solution rather than a medicine to cure the infection itself.
Q: How do I prepare Rice ORS 500 ml Saline correctly?
A: Dissolve the entire contents of one sachet of Rice ORS 500 ml Saline in the exact volume of clean, safe drinking water stated on the pack (commonly 200 mL, 500 mL, or 1 litre). Do not use less or more water than instructed, and do not add sugar, salt, milk, or juice. Use the solution within 24 hours and discard any leftover after that.
Q: Can Rice ORS 500 ml Saline be given to infants and young children?
A: Yes, Rice ORS 500 ml Saline is appropriate and recommended for infants (including newborns) and young children with diarrhea, given in small frequent amounts by clean cup and spoon. However, if an infant shows signs of severe dehydration (lethargy, sunken eyes, very little urine, unable to keep fluids down), seek immediate medical attention, as intravenous fluids may be needed.
Q: Is Rice ORS 500 ml Saline safe during pregnancy and breastfeeding?
A: Rice ORS 500 ml Saline is generally considered safe during pregnancy and breastfeeding, as oral rehydration is standard management for dehydration in these situations. A pregnant or breastfeeding woman with diarrhea or vomiting should still consult a physician, especially if symptoms are severe or persistent.
Q: What happens if Rice ORS 500 ml Saline is prepared too concentrated or given in excess?
A: Giving Rice ORS 500 ml Saline that is prepared with too little water, or in excessive volumes (especially in infants or people with kidney problems), can cause electrolyte imbalances such as hypernatremia or hyperkalemia, which may cause irritability, weakness, or in serious cases seizures. If this is suspected, stop giving the solution and seek immediate medical attention or contact a poison control center.
Q: When should I stop using Rice ORS 500 ml Saline and see a doctor instead?
A: Stop relying on Rice ORS 500 ml Saline alone and seek urgent medical care if there is severe dehydration (lethargy, sunken eyes, minimal urine output, inability to keep fluids down), persistent vomiting preventing oral intake, blood in the stool, high fever, signs of shock, or diarrhea lasting more than a few days, since these situations may need intravenous fluids or other treatment beyond oral rehydration.
Disclaimer
The information provided is accurate to the best of our knowledge, but it does not replace professional medical advice. We cannot guarantee its completeness or accuracy, and the absence of specific information about a drug should not be taken as an endorsement. We are not responsible for any consequences arising from this information, so please consult a healthcare professional for any concerns or questions.
